Medicine reading guide
Glipizide
Sulfonylurea for type 2 diabetes
Adults using immediate-release, single-ingredient glipizide oral tablets. This guide excludes extended-release (ER/XL), children and combination products.
Educational information. Independent clinical review pending. This is a selective explanation, not the full prescribing information.
Uses / Symptoms
- Type 2 diabetes, alongside diet and exercise.
Effects
- Stimulates pancreatic insulin release.
- Lowers blood sugar.
Side effects
- Digestive upset, dizziness or skin reactions.
- Low blood sugar can be severe.
Selected information; not a complete safety list. Full prescribing information and patient guidance ↗
How it works
Glipizide prompts the pancreas to release more insulin, which lowers blood sugar. It needs working insulin-producing cells and can sometimes push blood sugar too low.
Perspective answer sources
Section-two answers source-checked October 17, 2026; independent clinical review pending.
Read the mechanism, step by step
Glipizide stimulates pancreatic beta cells to release insulin. Functioning beta cells are needed for this effect.
Insulin release around meals increases. The label says the full long-term mechanism is not clearly established.
Insulin stimulation can lower glucose too far, especially with inadequate food, prolonged exercise, alcohol or other glucose-lowering medicines.
Common questions
What is it for?
It improves blood-sugar control in adults with type 2 diabetes, alongside diet and exercise.
How does it work?
It stimulates insulin release; the pancreas must still have functioning beta cells.
Is this the same as glipizide ER or XL?
No. Regular and extended-release tablets have different administration instructions. Confirm your formulation with the pharmacist.
Does it treat type 1 diabetes?
No. It must not be used for type 1 diabetes or diabetic ketoacidosis.
What side effects might I notice?
Diarrhea, gas, dizziness or skin reactions can occur. Report persistent symptoms; shaking or jitteriness can also accompany low glucose.
Can blood sugar fall too low?
Yes. Agree a low-glucose recognition and treatment plan with your care team, and share it with caregivers. Follow that plan immediately if symptoms occur. Kidney or liver disease can prolong an episode.
When should I get urgent help?
Call emergency services for collapse, seizures or inability to awaken. Contact your doctor immediately for yellow skin or eyes, dark urine or unusual bruising.
Can other medicines interact?
Yes. Review prescriptions, supplements and over-the-counter drugs, including aspirin, ibuprofen and naproxen. Do not add them without checking.
How will I know it helps?
Check glucose as instructed and keep laboratory appointments. HbA1c helps assess longer-term control.
What does the heart warning mean?
The label carries a cardiovascular-mortality warning based on an older study of another sulfonylurea. Discuss benefits, risks and alternatives.
What if I become ill?
Ask for an illness or surgery plan. Fever, infection or injury can change glucose control.
What about pregnancy or breastfeeding?
Tell your prescriber if pregnant, planning pregnancy or breastfeeding; treatment needs individual review.
Animation chapters, evidence & visual limits
Adults using immediate-release, single-ingredient oral glipizide for type 2 diabetes. Excludes ER/XL, children, combination products and dosing instructions.
Educational draft; independent clinical review pending. Cell, ion and protein symbols are original schematics, not atomic models or measured traces. The selected DailyMed source is a repackager label; originating-label equivalence has not been established. Recombinant channel and rodent-islet experiments inform the pathway but do not predict individual human responses. The immediate-release label says the complete long-term glucose-lowering mechanism is not clearly established.
Original conceptual illustrations. AI-assisted editorial source check; independent clinical review pending. No recorded narration.
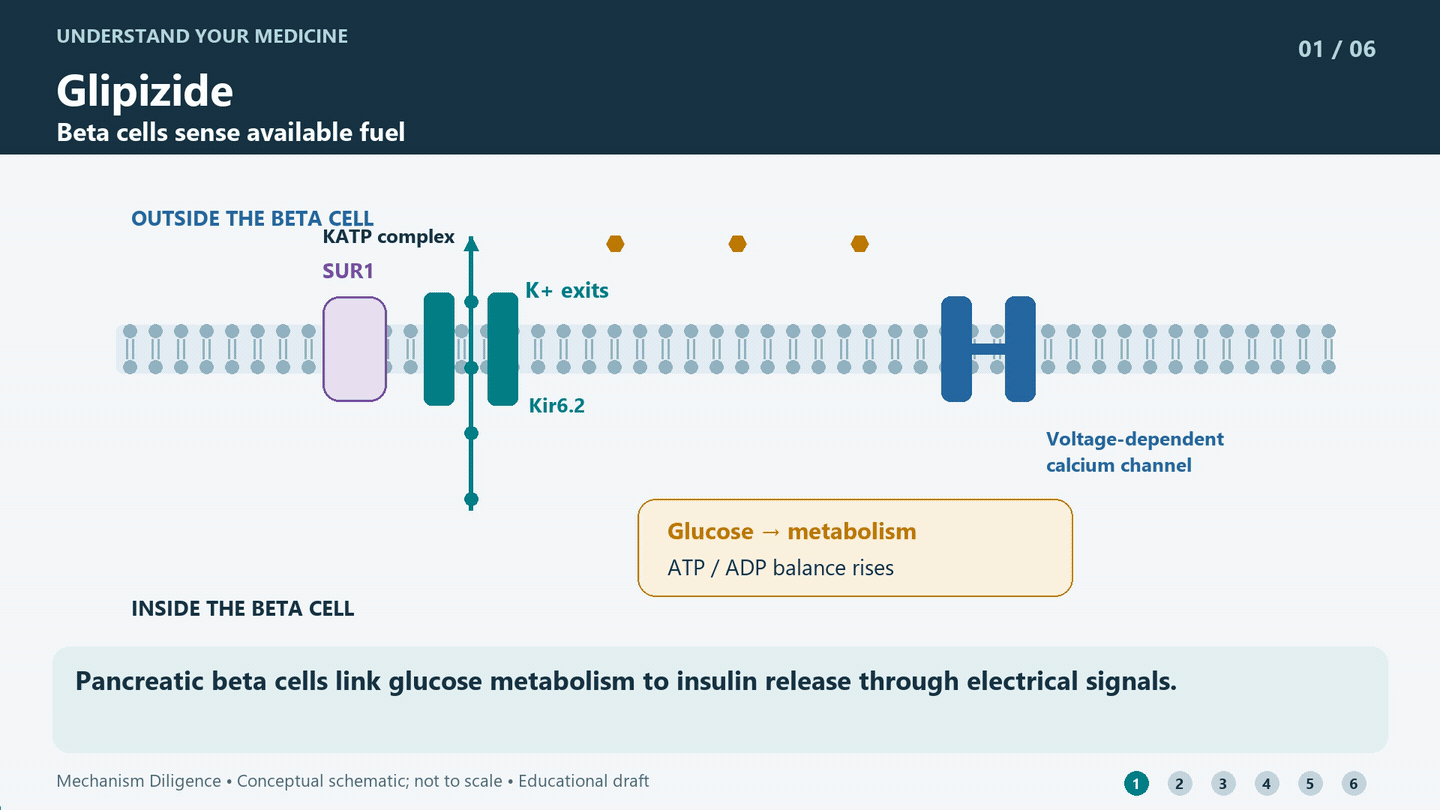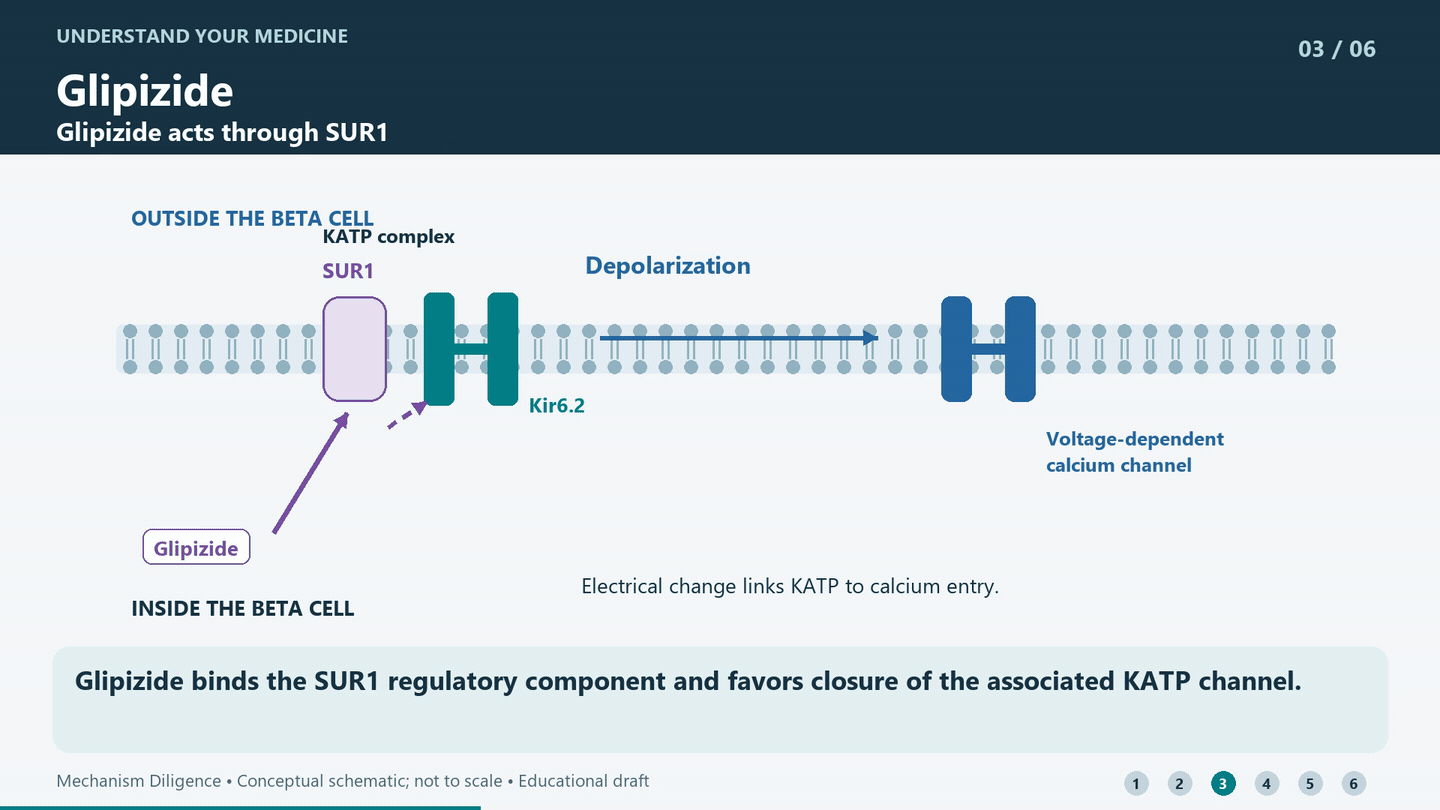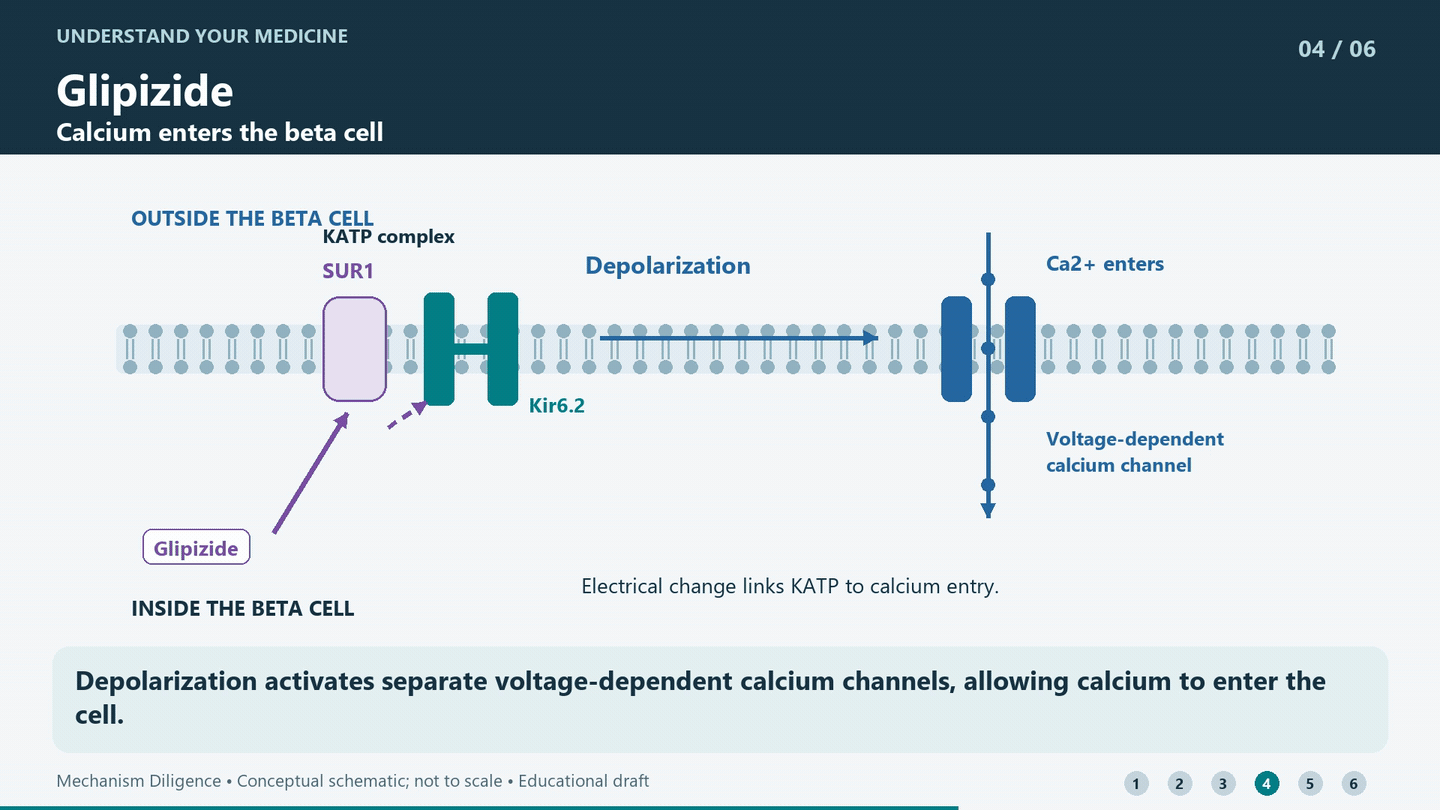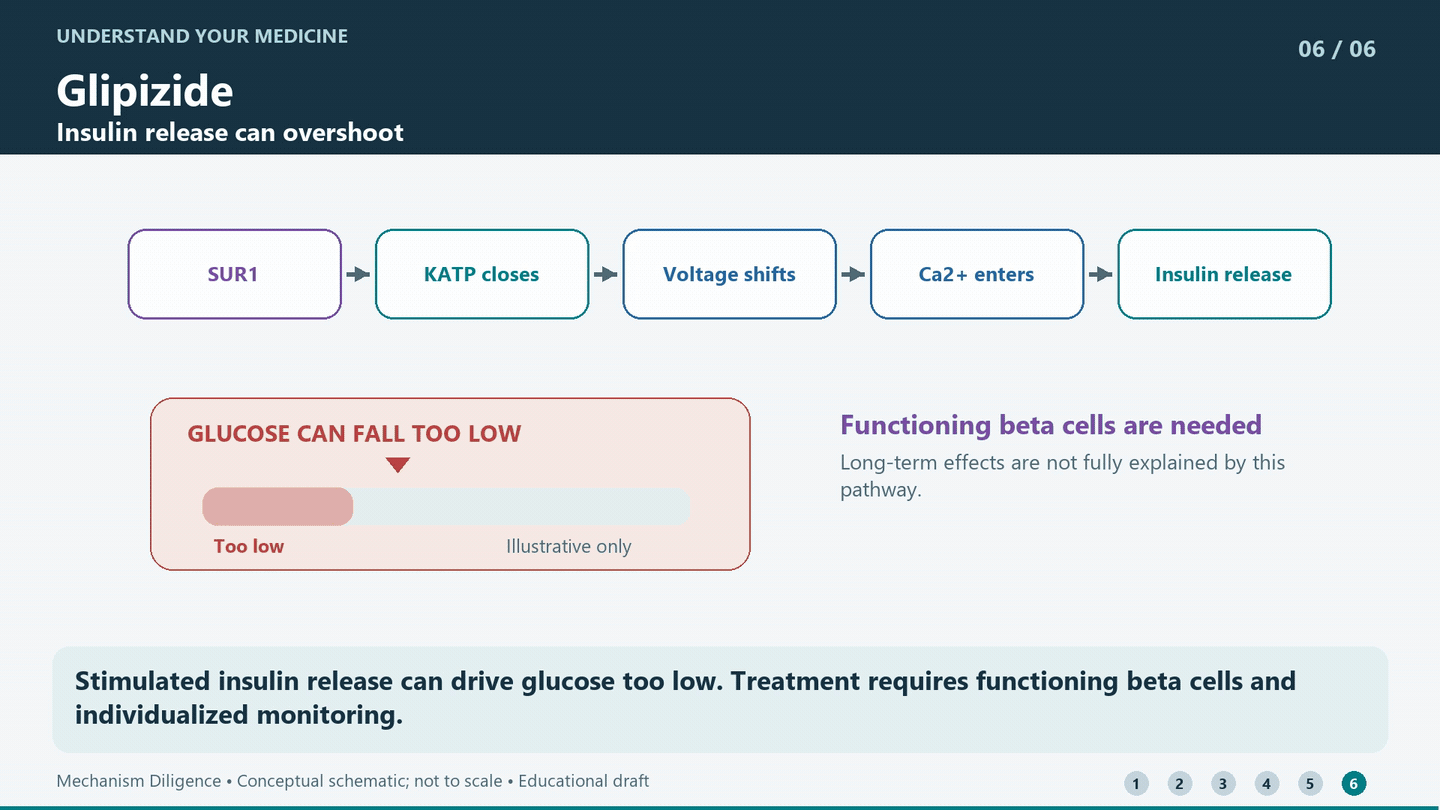
Chapter 1: Beta cells sense available fuel
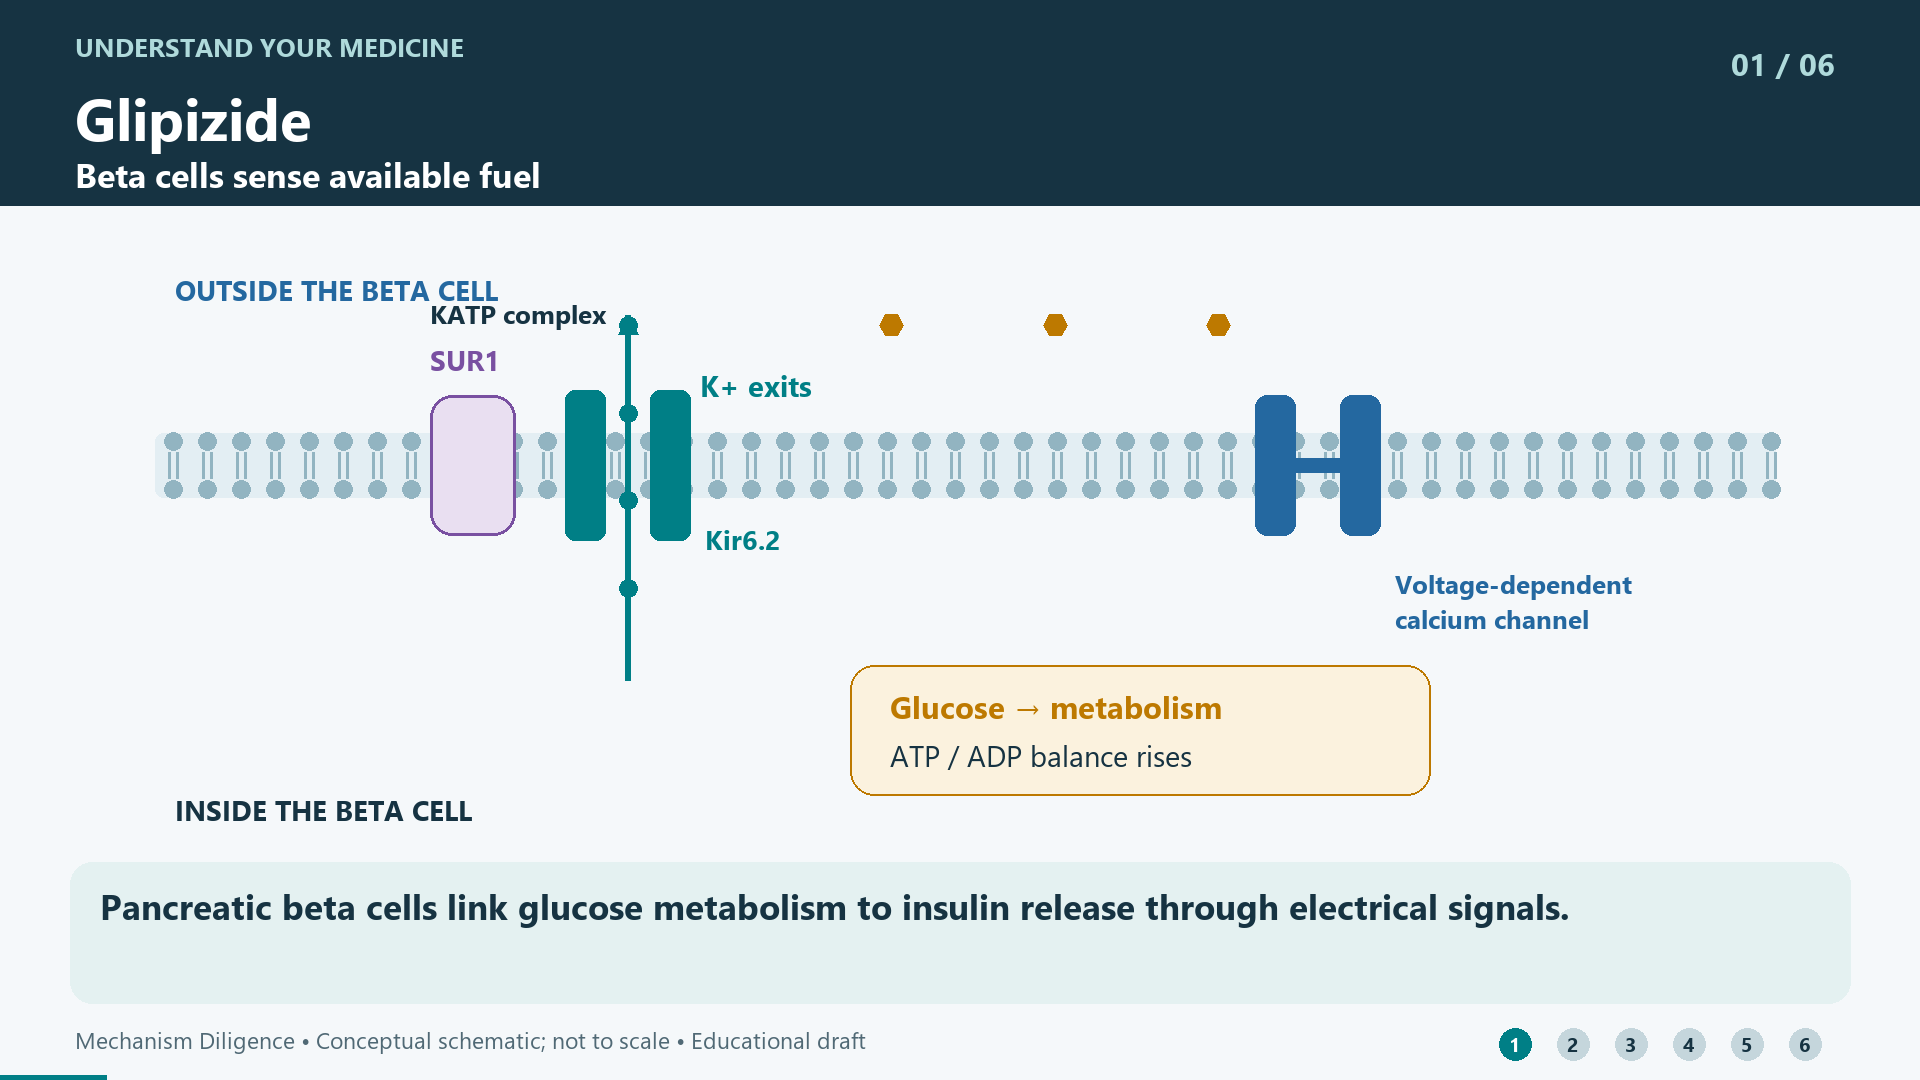
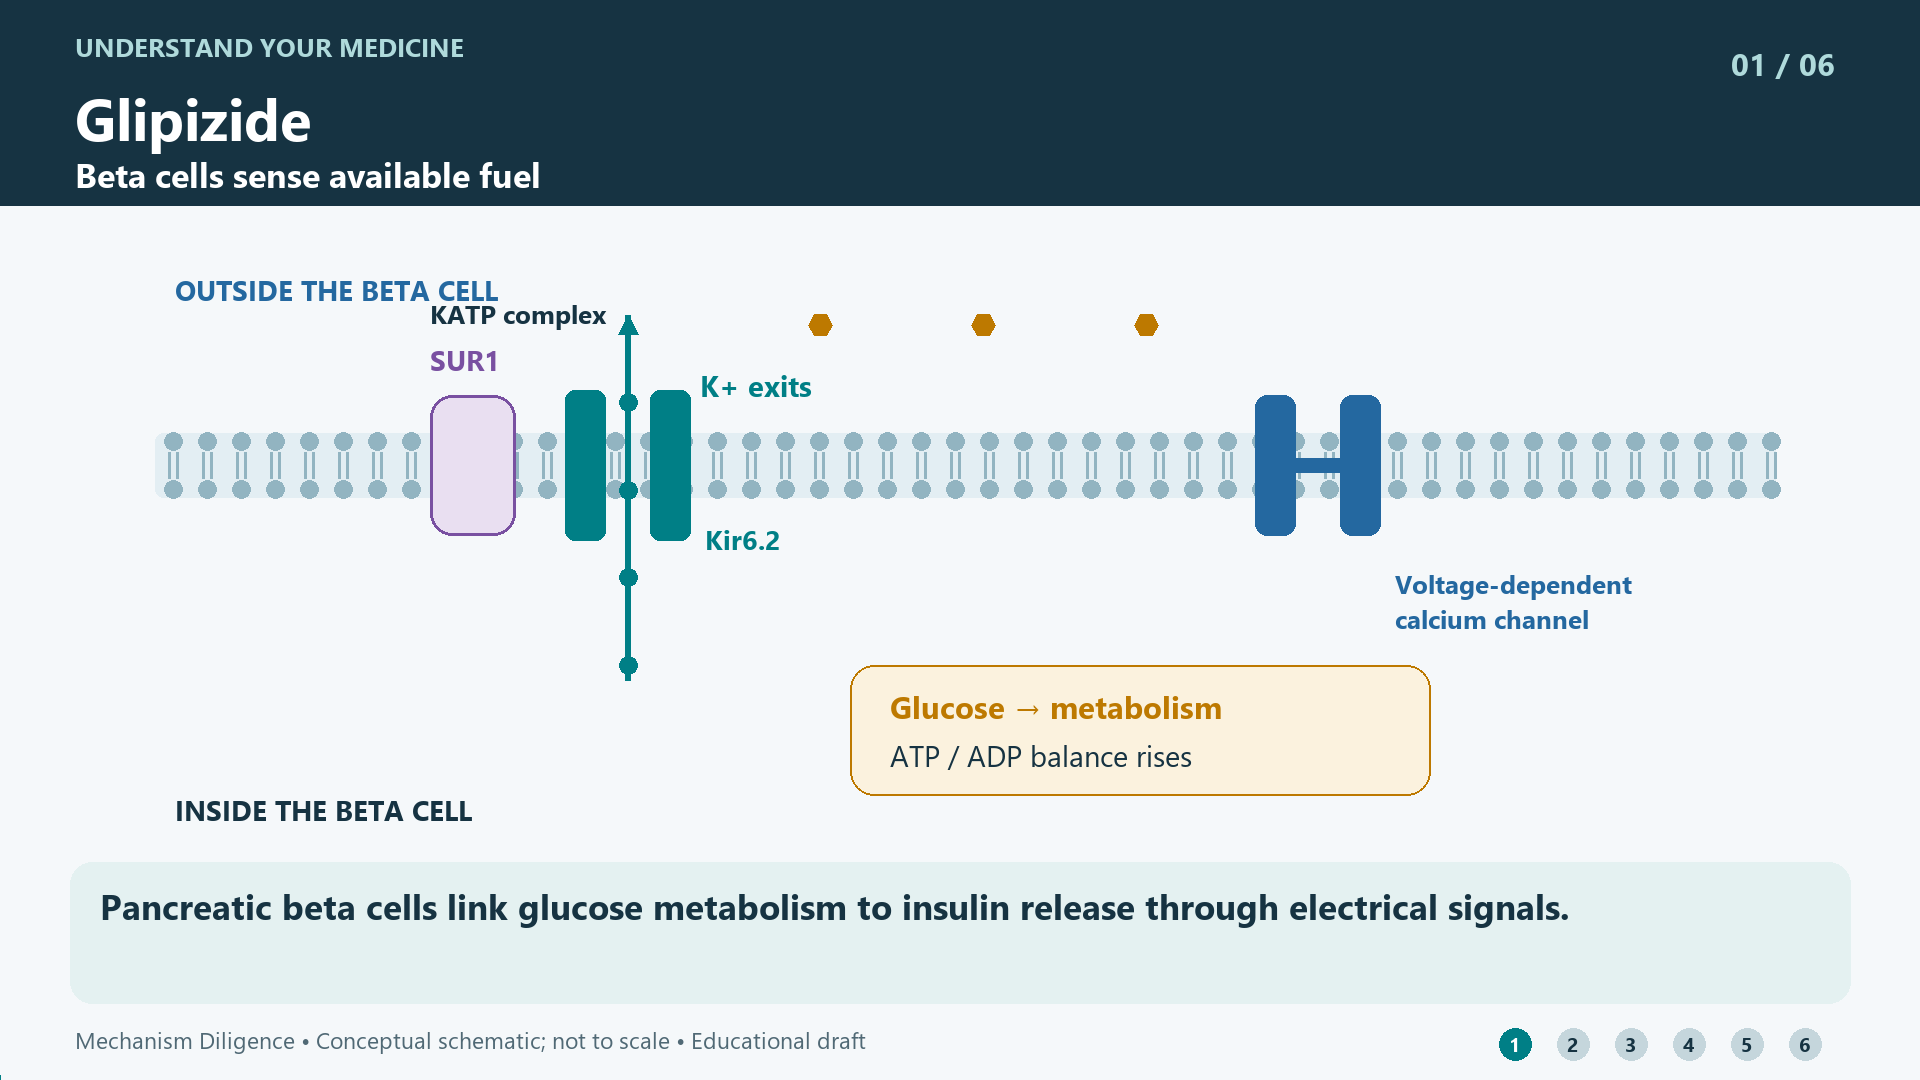
Pancreatic beta cells link glucose metabolism to insulin release through electrical signals.
In the canonical triggering pathway, glucose metabolism raises the cellular ATP-to-ADP balance. ATP-sensitive potassium channels couple that metabolic state to membrane voltage. This baseline sequence helps explain why changing a potassium channel can affect insulin release.
This is the triggering arm of insulin secretion. Other metabolic, hormonal and neural amplification pathways are omitted.
- Pharmacology of human SUR1/Kir6.2 expressed in HEK-293 cells · Abstract; Introduction; ligand-binding results and Discussion · Primary recombinant human channel pharmacology; indexed text inspected · checked 2026-10-17
Chapter 2: Fuel changes the electrical signal
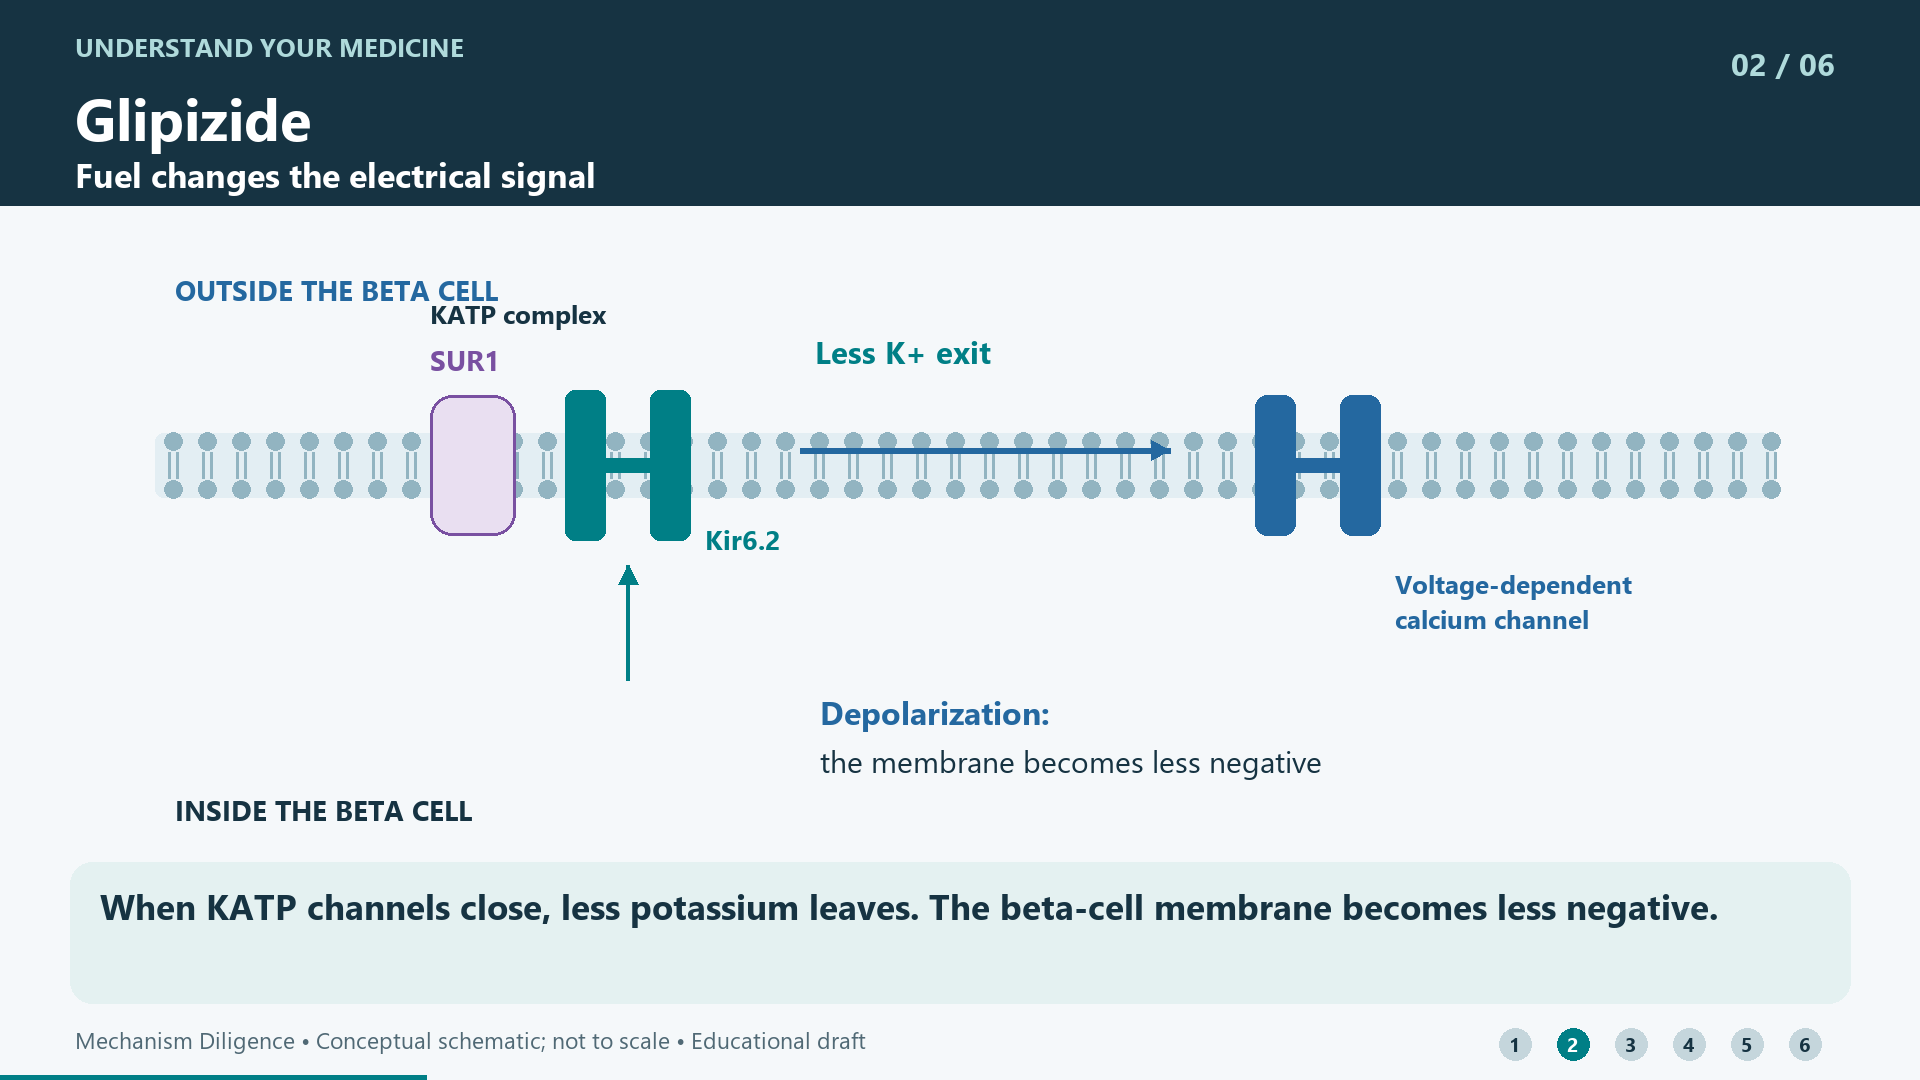
When KATP channels close, less potassium leaves. The beta-cell membrane becomes less negative.
The beta-cell KATP complex includes the Kir6.2 potassium-conducting pore and regulatory SUR1. Lower potassium conductance favors depolarization. A reduction in outward K+ movement is therefore the key electrical step; it is not sodium pumping or direct calcium transport by KATP.
Channel opening is probabilistic and voltage depends on multiple currents. The open/closed gate is a simplified teaching device.
- Pharmacology of human SUR1/Kir6.2 expressed in HEK-293 cells · Abstract; Introduction; ligand-binding results and Discussion · Primary recombinant human channel pharmacology; indexed text inspected · checked 2026-10-17
- Iterative stimulation of pancreatic islets by glipizide · Abstract: rubidium/calcium flux, insulin release and interpretation · Primary isolated rat-islet experiment; abstract inspected · checked 2026-10-17
Chapter 3: Glipizide acts through SUR1
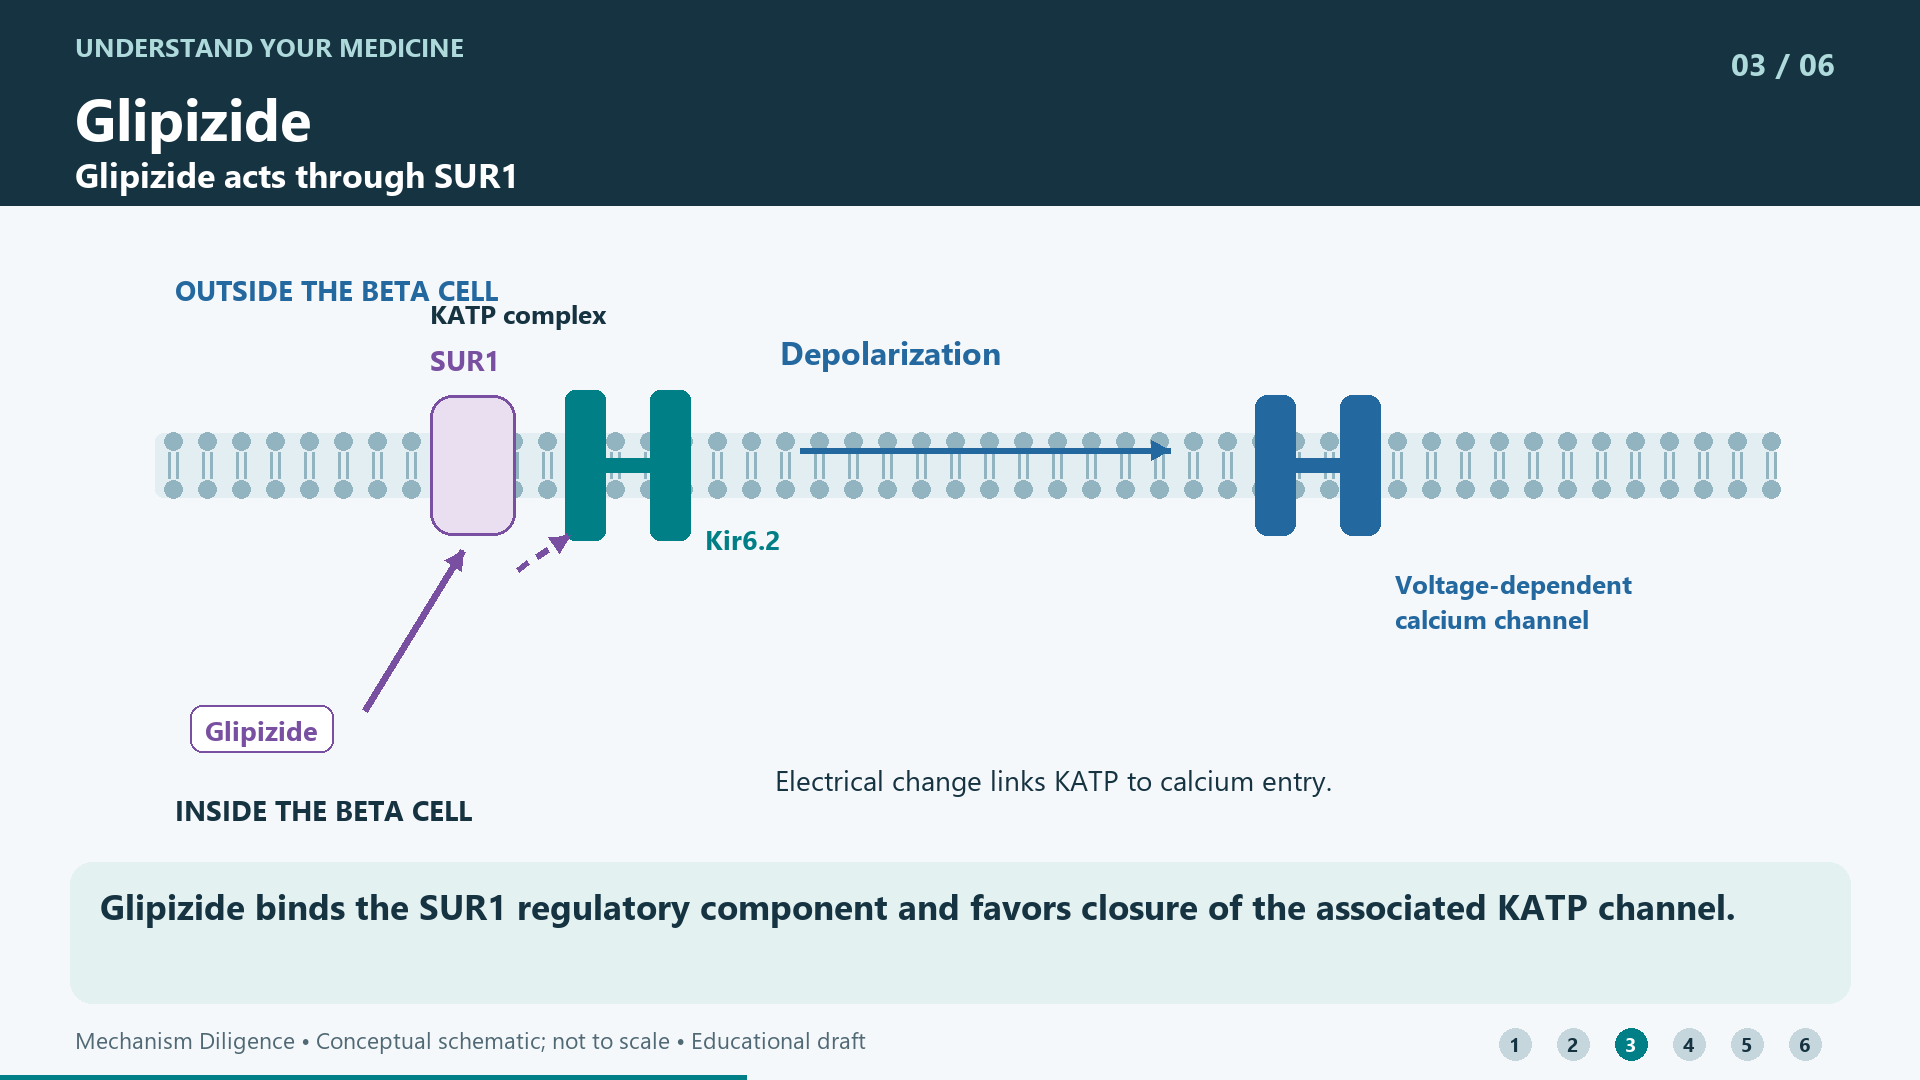
Glipizide binds the SUR1 regulatory component and favors closure of the associated KATP channel.
Glipizide binding was demonstrated in recombinant human SUR1/Kir6.2 pharmacology. Its electrical action converges on reduced potassium conductance, as supported by isolated-islet experiments. Glipizide is neither insulin nor a potassium-pore plug, and a symbolic SUR1 docking point is not an experimentally rendered binding pose.
The diagram shows the main secretory pathway; recombinant binding assays alone are not direct measurements of beta-cell activity in a treated person.
- Pharmacology of human SUR1/Kir6.2 expressed in HEK-293 cells · Abstract; Introduction; ligand-binding results and Discussion · Primary recombinant human channel pharmacology; indexed text inspected · checked 2026-10-17
- Iterative stimulation of pancreatic islets by glipizide · Abstract: rubidium/calcium flux, insulin release and interpretation · Primary isolated rat-islet experiment; abstract inspected · checked 2026-10-17
Chapter 4: Calcium enters the beta cell
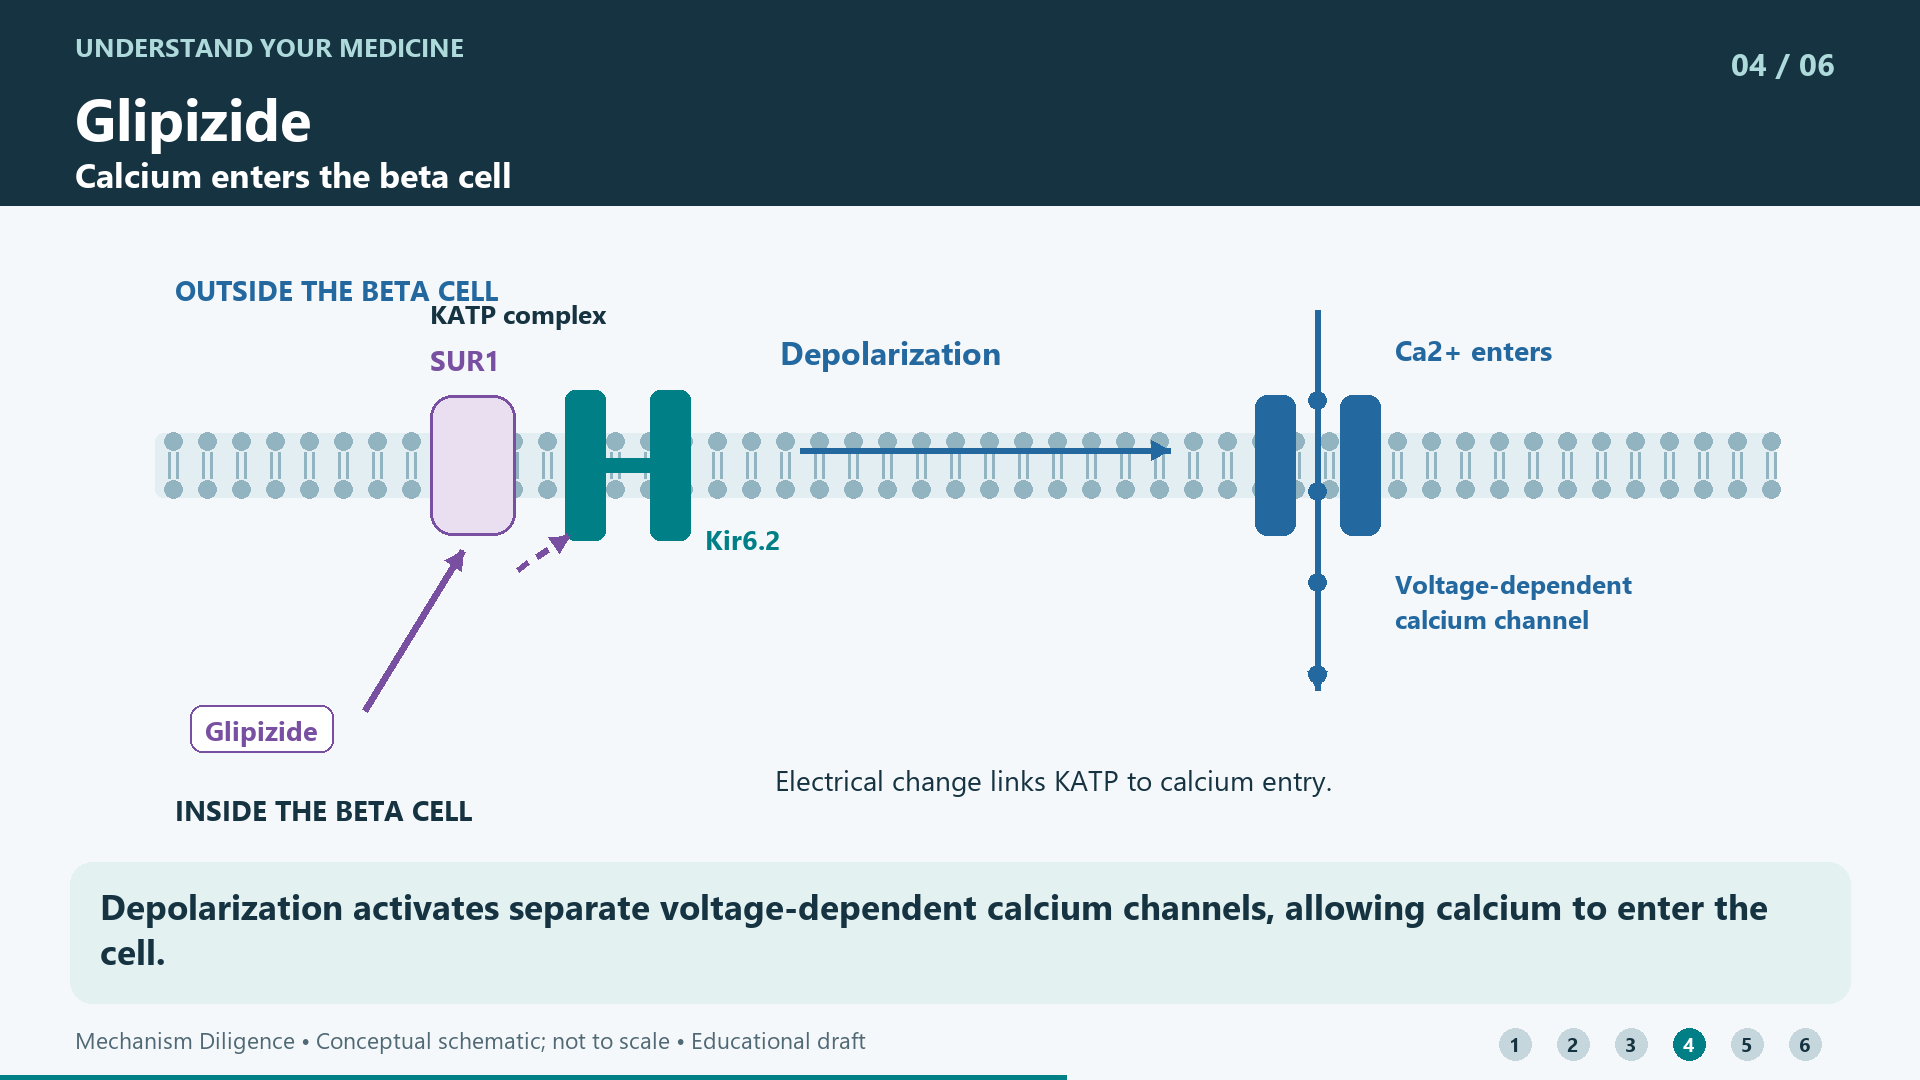
Depolarization activates separate voltage-dependent calcium channels, allowing calcium to enter the cell.
The voltage change links KATP inhibition to calcium influx. Glipizide experiments in isolated rat islets support this sequence, while human beta-cell work shows that multiple voltage-operated calcium-channel components contribute to insulin secretion. Glipizide is not depicted as binding the calcium channel directly.
A single calcium gate stands for multiple channel subtypes. Experimental timing and concentrations are not reproduced.
- Iterative stimulation of pancreatic islets by glipizide · Abstract: rubidium/calcium flux, insulin release and interpretation · Primary isolated rat-islet experiment; abstract inspected · checked 2026-10-17
- Voltage-operated calcium channels and glucose-induced insulin release from human beta cells · Abstract: human beta-cell calcium entry and insulin secretion · Primary human-cell/islet physiology; abstract inspected, not a glipizide trial · checked 2026-10-17
Chapter 5: Insulin granules release their cargo
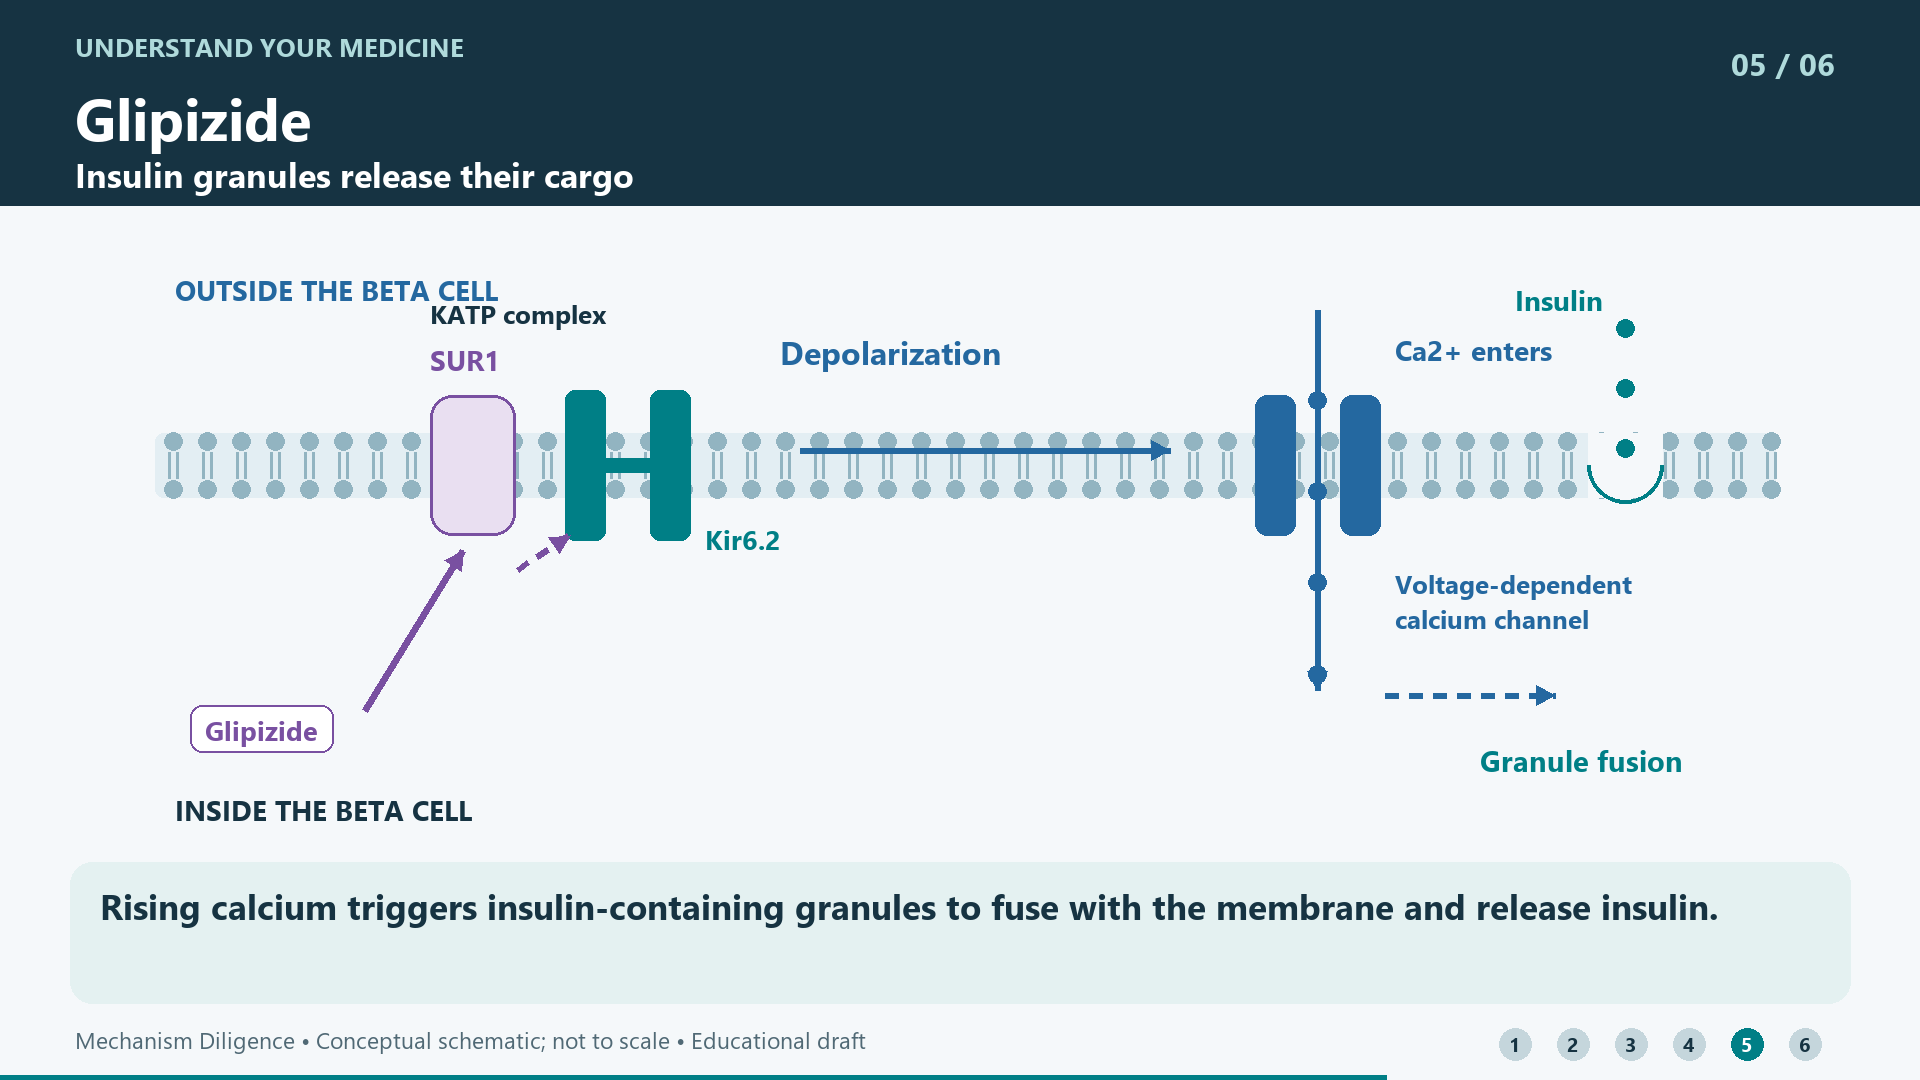
Rising calcium triggers insulin-containing granules to fuse with the membrane and release insulin.
Calcium-dependent exocytosis connects the electrical signal to secretion. Membrane-capacitance experiments in mouse beta cells directly tracked this process; human-cell physiology supports the calcium–secretion link. Functioning pancreatic beta cells are necessary for glipizide's acute glucose-lowering effect.
Granule recruitment, priming and recycling are simplified. Mouse-cell exocytosis data do not specify the magnitude of a human treatment response.
- Ammala et al. — Exocytosis elicited by calcium currents in mouse pancreatic beta cells · Abstract: membrane capacitance, calcium dependence and granule release; DOI 10.1113/jphysiol.1993.sp019966 · Primary mouse beta-cell electrophysiology; abstract inspected · checked 2026-10-17
- Voltage-operated calcium channels and glucose-induced insulin release from human beta cells · Abstract: human beta-cell calcium entry and insulin secretion · Primary human-cell/islet physiology; abstract inspected, not a glipizide trial · checked 2026-10-17
- Glipizide immediate-release prescribing information — DailyMed / PD-Rx · Clinical Pharmacology: Mechanism of Action; Indications; Contraindications; Precautions: Hypoglycemia · US repackager prescribing information; selected sections inspected · checked 2026-10-17
Chapter 6: Insulin release can overshoot
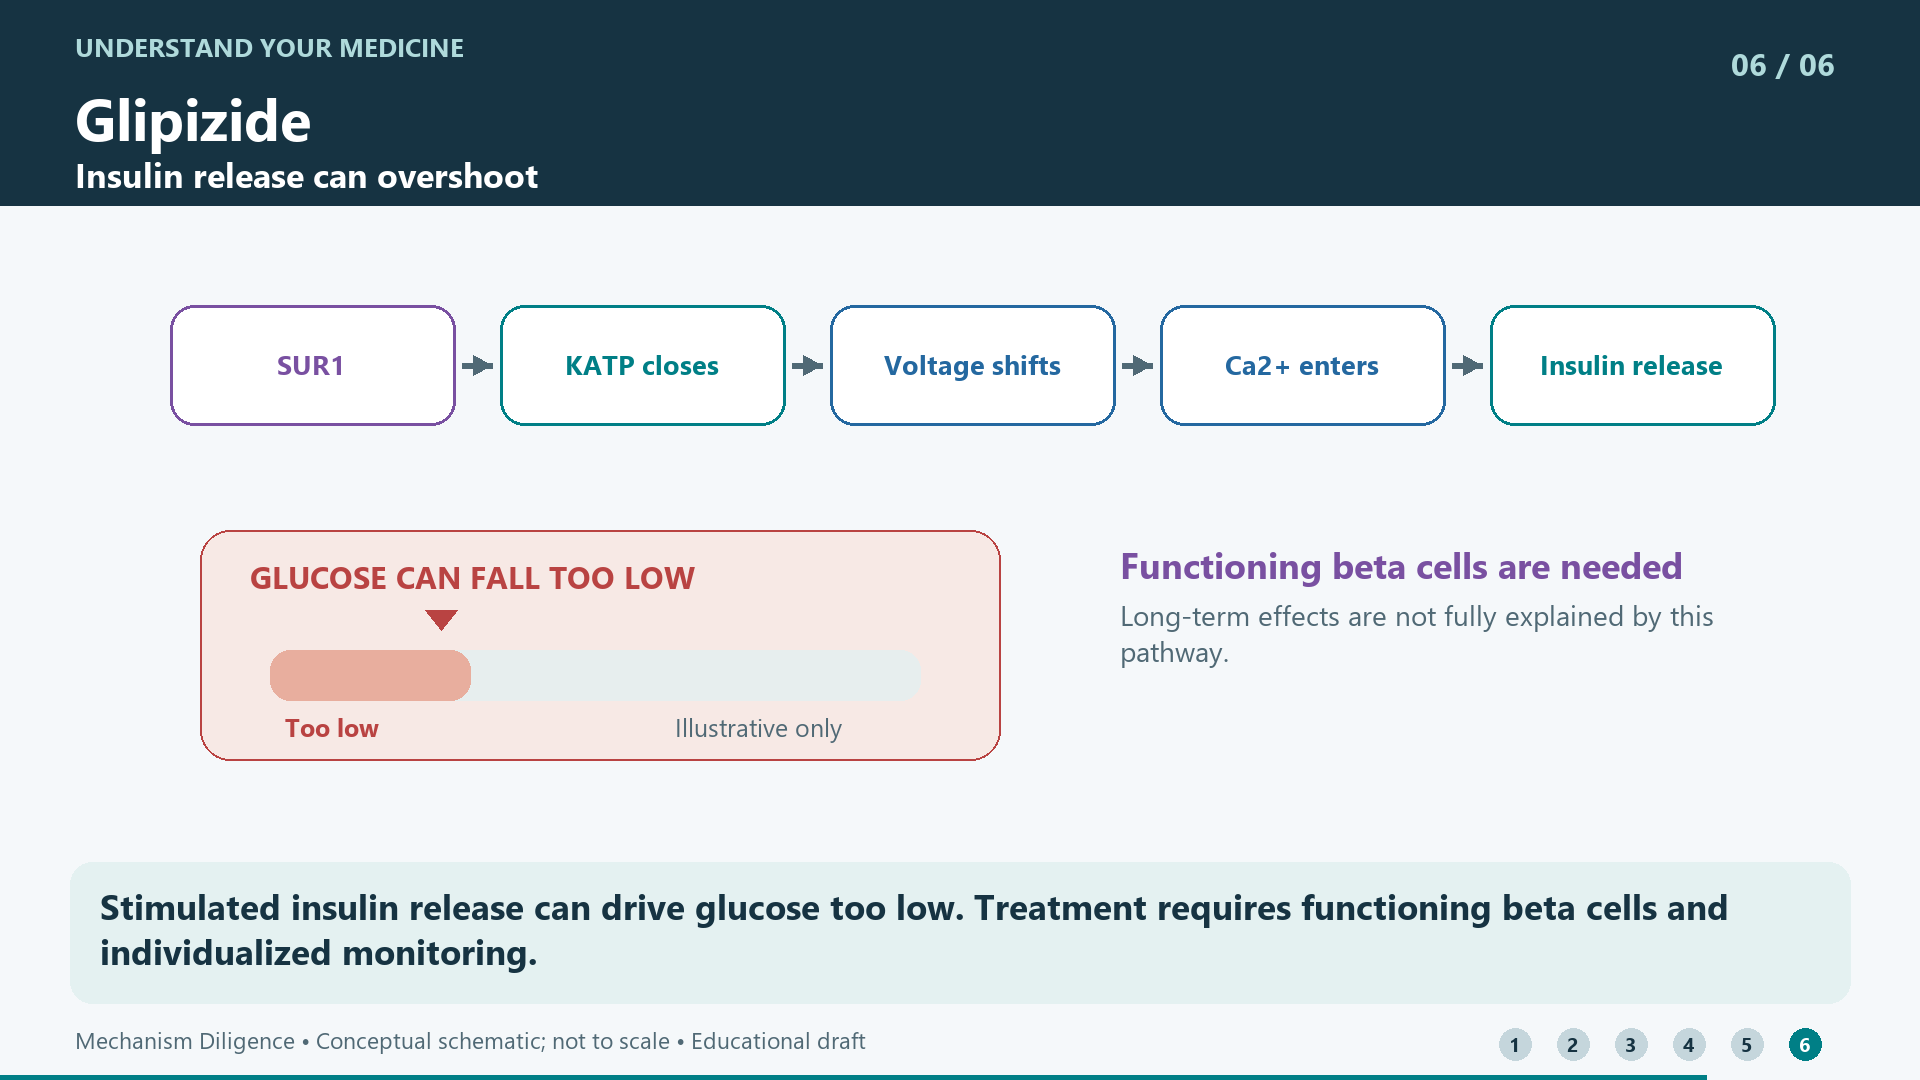
Stimulated insulin release can drive glucose too low. Treatment requires functioning beta cells and individualized monitoring.
Glipizide can cause severe hypoglycemia, with risk influenced by factors such as inadequate food and other glucose-lowering medicines. The immediate-release label leaves the full long-term mechanism unresolved. This pathway neither explains every chronic effect nor establishes a cardiovascular benefit.
Do not imply the medicine releases insulin only when glucose is high, repairs beta cells, cures diabetes or guarantees ongoing effectiveness.
- Glipizide immediate-release prescribing information — DailyMed / PD-Rx · Clinical Pharmacology: Mechanism of Action; Indications; Contraindications; Precautions: Hypoglycemia · US repackager prescribing information; selected sections inspected · checked 2026-10-17
- Pharmacology of human SUR1/Kir6.2 expressed in HEK-293 cells · Abstract; Introduction; ligand-binding results and Discussion · Primary recombinant human channel pharmacology; indexed text inspected · checked 2026-10-17
Sources & scope
Source pages checked 2026-10-12. AI editorial source check; independent clinical review pending.
- Adult, single-ingredient scope only.
- No dose, regimen, switching or individual treatment advice.
- Selective safety summary; consult the full label and your care team.
- Source mapping is not independent clinical review.
- The cited DailyMed record is a repackager label; originating-label equivalence has not been verified.
DailyMed / NLM ↗ · PD-Rx Pharmaceuticals, Inc. · page updated 2025-10-20